

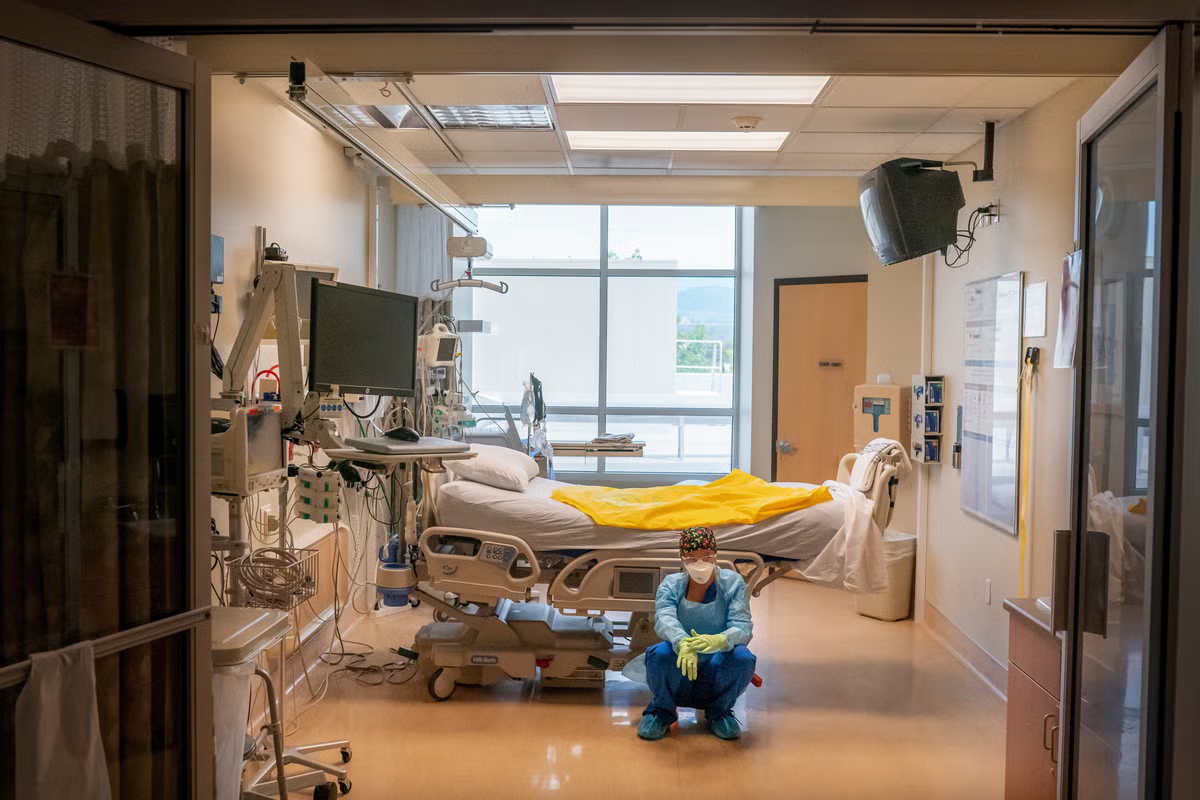
Even as automation fears loom large across the modern labor market, the United States faces a different kind of crisis in one of its most secure professions. Registered nurses earn a median annual salary of $97,550, and because their direct, hands-on care cannot easily be replaced by artificial intelligence, nursing school enrollments remain robust. Yet data show that qualified healthcare professionals are walking away from hospital floors of their own accord, driven by heavy workloads, chronic understaffing, and escalating physical violence.
Annual turnover rates for bedside registered nurses reached 18 percent last year, marking a significant increase from 11 percent a decade and a half ago, according to figures from the nurse-placement firm NSI Nursing Solutions. A broader industry survey of 800,000 nurses revealed that approximately 40 percent plan to retire or leave the workforce within five years, citing relentless stress and understaffing. Industry specialists emphasize that this high attrition rate stems from working conditions rather than an absolute shortage of trained professionals.
Jeff Doucette, chief nursing officer at healthcare analytics firm Press Ganey, noted that the country does not lack nurses, but rather lacks nurses willing to work in the current environment. Health executives warn that the departure of experienced staff inflicts severe damage on operational efficiency and patient safety, compounding the risks of medical errors and falls. Senior nurses have traditionally provided crucial mentoring and rapid diagnostic assessments on busy hospital floors.
Dustin Bass, president of the Emergency Nurses Association, pointed to a generational shift in hospital staffing. A decade ago, veteran nurses with 10 to 20 years of experience managed triage departments and could spot severe medical conditions across a crowded room. Today, nurses with only two or three years of experience are left running massive emergency rooms with more than 130 care spaces.

Structural changes in healthcare delivery have intensified these pressures. While routine recoveries have largely shifted to outpatient care, hospitalized patients today are typically sicker and require complex, intensive treatment. Simultaneously, severe staffing shortages and a lack of available hospital beds have created chronic backlogs, leaving patients waiting in corridors for extended periods. Data analyzed by the University of Michigan Medical School and Beth Israel Deaconess Medical Center indicate that emergency room wait times spiked during the pandemic and remained high through 2024, with nearly 5 percent of winter patients waiting more than 24 hours for an inpatient bed.
This severe overcrowding frequently boils over into physical aggression against healthcare workers. Data compiled by Press Ganey show that 2.4 percent of nursing personnel experienced a physical assault last year, representing a 26 percent increase since 2017 and translating to more than 1,000 reported incidents per month. Union surveys suggest the true numbers are even higher. A National Nurses United poll of 1,300 nurses found that 33 percent reported being slapped, punched, or kicked over the prior year, while 12 percent reported being groped or inappropriately touched.

Juliet Etienne, a 29-year-old emergency department nurse in New Orleans, explained that nurses often bear the brunt of patients’ frustrations because they serve as the face of the hospital, held accountable for systemic delays outside their control. Amy Stimpfel, an associate professor at Villanova University’s M. Louise Fitzpatrick College of Nursing, observed that long delays directly fuel patient anger when vulnerable individuals find their call buttons unanswered.
For many practitioners, the physical threats and daily hazards make bedside nursing untenable. Paige Campbell, a 33-year-old nurse who entered the profession during the pandemic, worked in an emergency department in Fort Walton Beach, Florida. After enduring multiple incidents where she was kicked, spat on, and shoved, she left her bedside role last year when an aggressive patient strangled her after she offered him a blanket. Campbell subsequently transitioned to remote patient-monitoring to recover.

Expanded career alternatives give bedside nurses clearer exit paths than in prior decades, allowing many to transition to urgent care centers, virtual nursing, or independent nurse practitioner roles that offer higher pay and predictable hours. Christian Stone spent five years working in Washington, D.C., emergency rooms—where he was routinely yelled at and once bitten by a patient—before moving to an urgent care clinic where he no longer dreads going to work.
The financial toll of this turnover on healthcare facilities is substantial. Omid Razmpour, a researcher at Emory University and former ICU nurse, analyzed turnover at Emory Healthcare and calculated that losing a single nurse costs the system approximately $78,000 in recruitment, training, and temporary contract labor. To counter these expenses, Emory Healthcare invested $150 million in staff pay increases, primarily targeting nurses. Sharon Pappas, the system’s former chief nurse executive, noted that the investment ultimately saved money by successfully reducing turnover rates.
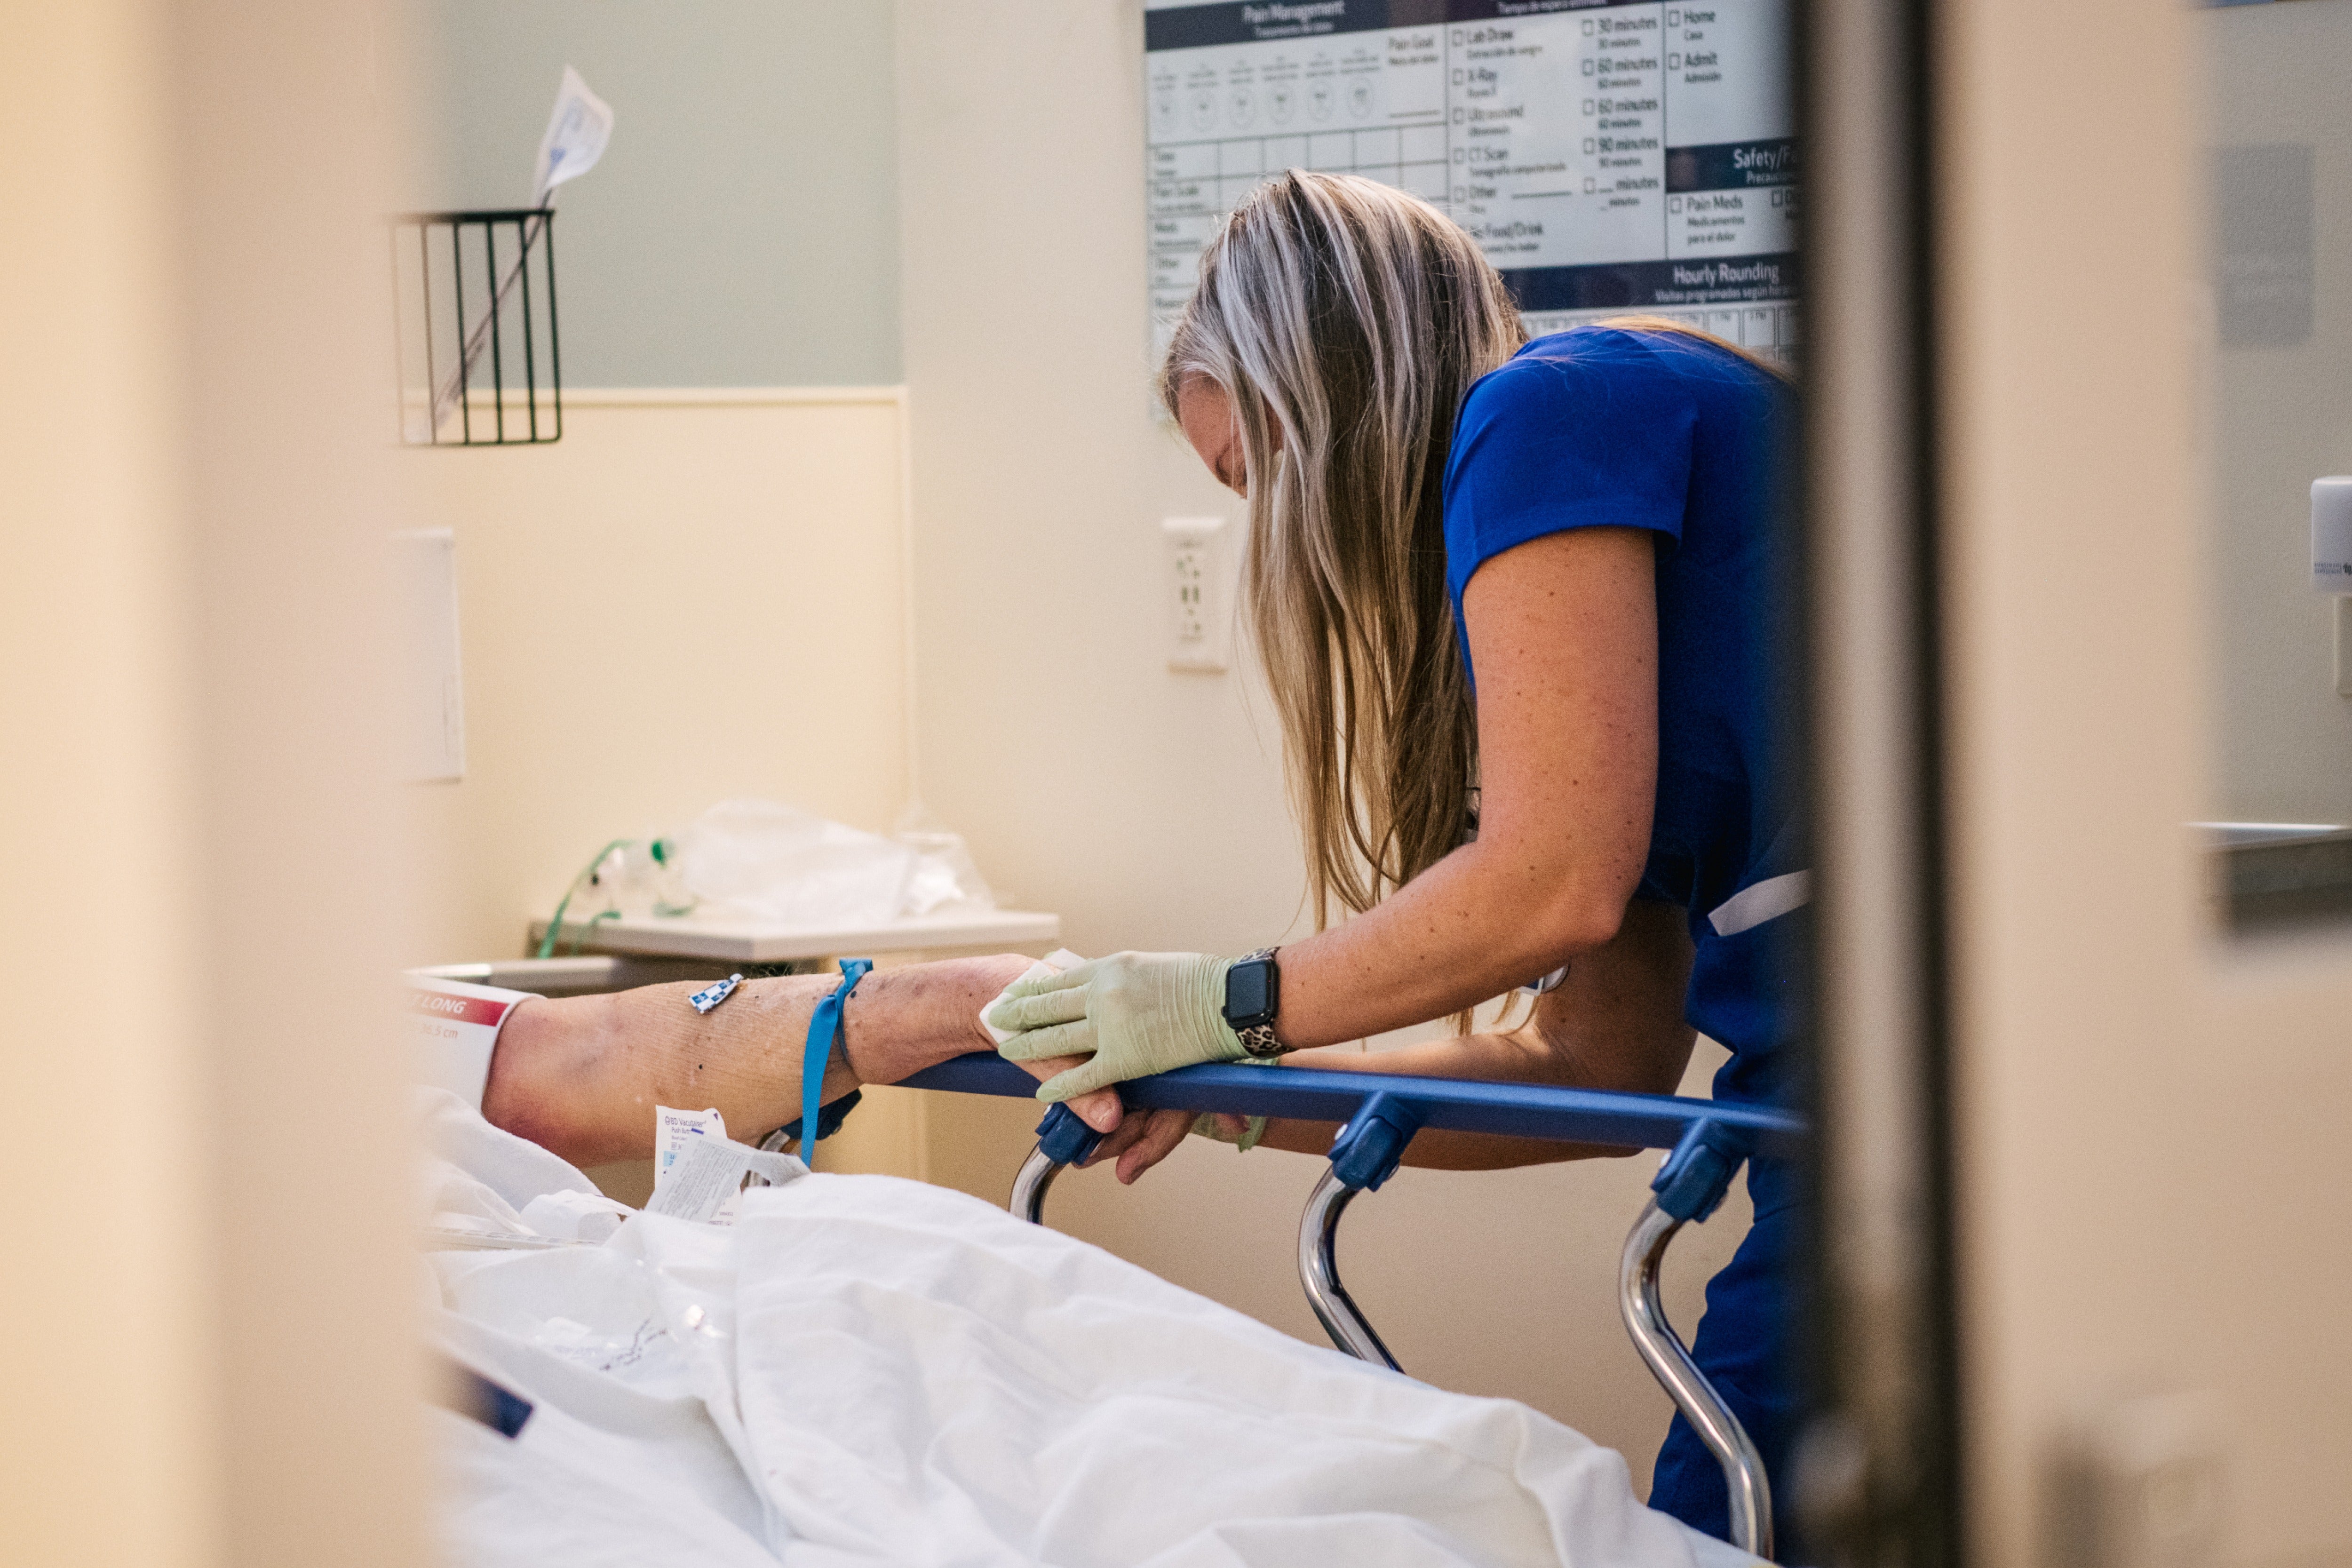
Hospitals nationwide are also investing heavily in physical security measures, including panic buttons, armed guards, and metal detectors. The University of Pittsburgh Medical Center installed security upgrades across 40 facilities following a fatal shooting at its campus in York, Pennsylvania. Maribeth McLaughlin, the hospital system’s chief nurse executive, noted that health networks across the country are rushing to implement these safeguards.
Nurses maintain that security hardware alone cannot solve the crisis unless matched by better staffing levels and robust safety policies. Despite surviving a near-fatal assault, Campbell and her colleagues recently voted to unionize their HCA Healthcare facility over safety concerns and overcrowding. Despite her trauma, Campbell plans to return to emergency department care, driven by a deep commitment to patient care.



